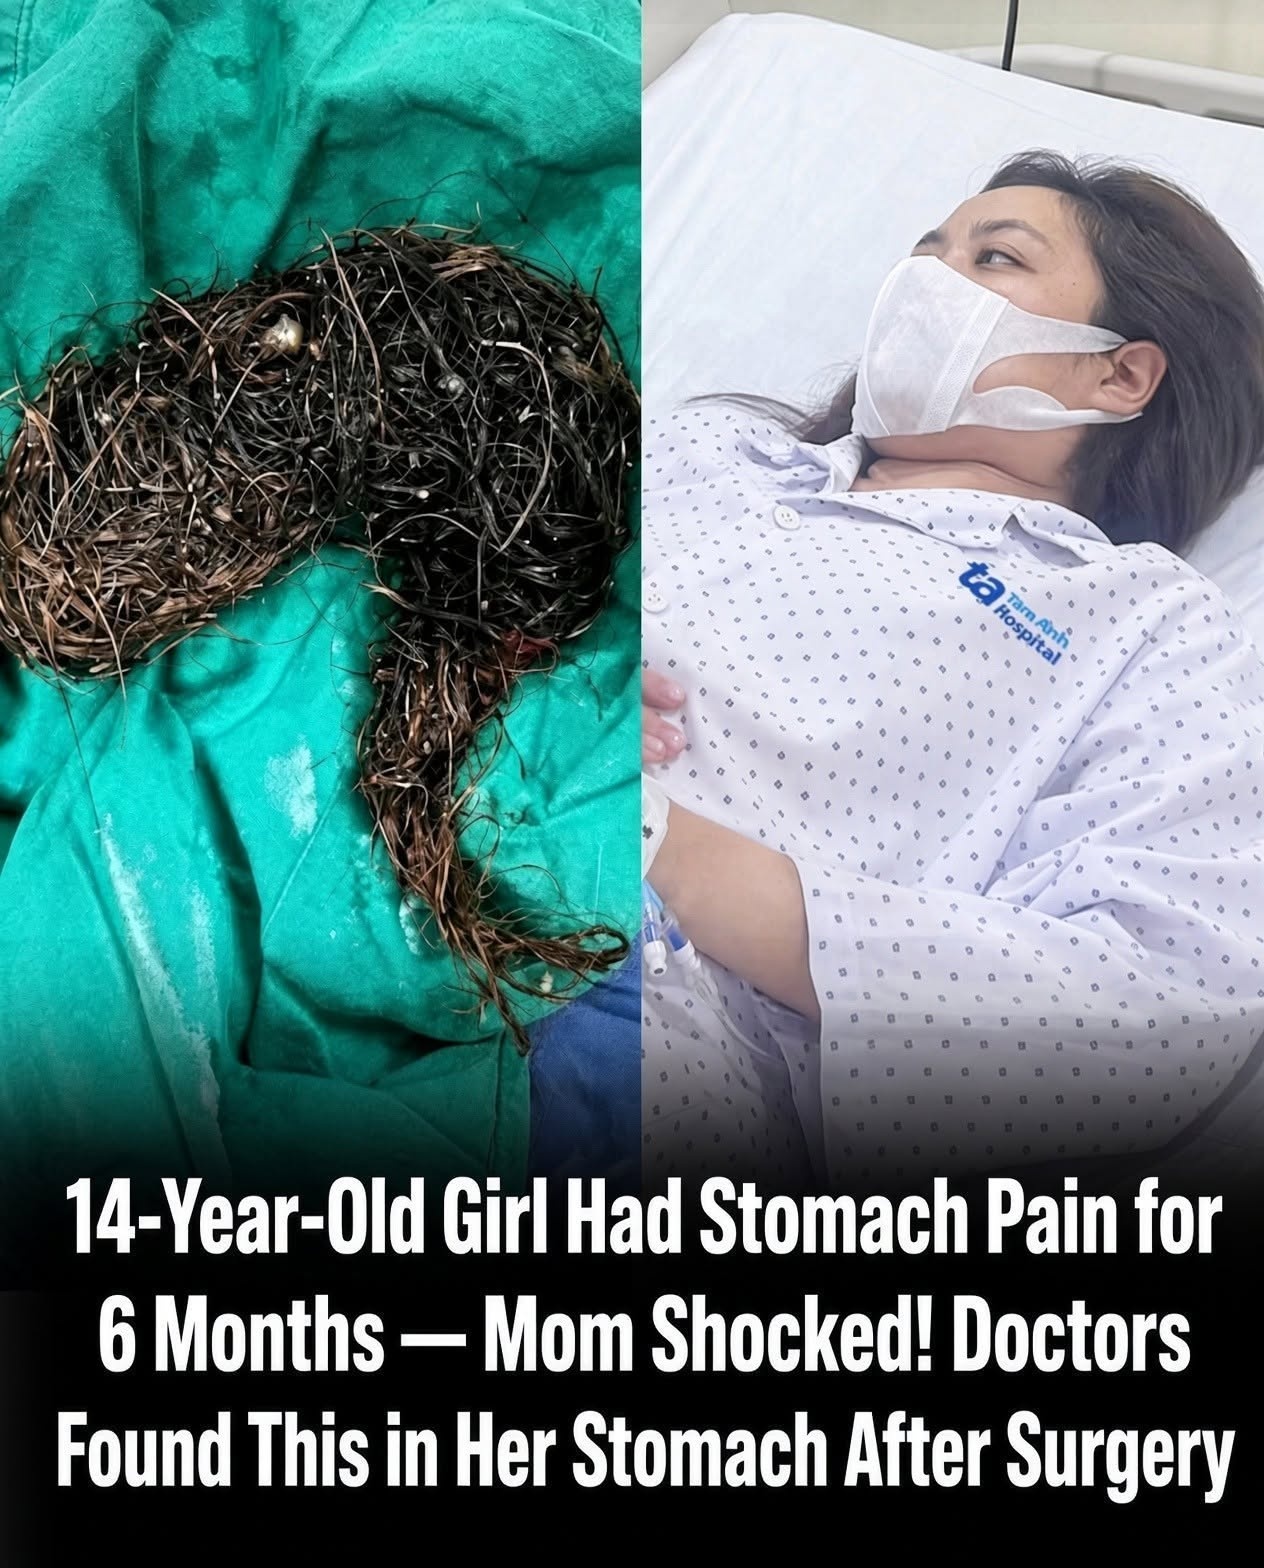
Months of unexplained abdominal pain can turn an ordinary teenager's life into a daily struggle. A disturbing medical story involving a 14-year-old girl has drawn attention to an uncommon digestive condition—and to the importance of recognizing symptoms that should never be ignored.
Chapter 1: Six Months of Pain and Unanswered Questions
For many teenagers, abdominal pain is an occasional inconvenience. It might appear after eating too quickly, during a minor illness, or because of temporary digestive discomfort. Usually, the symptoms gradually disappear, allowing life to return to normal.
But imagine experiencing that discomfort repeatedly for six months.
Imagine waking up in the morning wondering whether your stomach will hurt during school, whether you will be able to finish your lunch, or whether another evening will be spent curled up in bed instead of enjoying time with friends.
For a young person, ongoing pain can affect far more than physical comfort. It can interfere with concentration, appetite, sleep, confidence, and the simple activities that make adolescence enjoyable.
A widely circulated story describes a 14-year-old girl who reportedly experienced abdominal pain for approximately six months before doctors discovered something unexpected during surgery. The accompanying photograph suggests an unusual mass inside the digestive tract, prompting questions about how such a condition could develop and why its symptoms might persist.
However, an important distinction must be made from the beginning: the available headline and photographs do not independently establish the girl's medical history, the precise surgical findings, or the final diagnosis. Without an identifiable hospital report, medical case publication, or verified statement from the treating team, those details should not be presented as confirmed facts.
Nevertheless, the reported circumstances highlight a genuine and important medical issue. Persistent abdominal pain in children and adolescents can sometimes indicate conditions that require specialized investigation, and rare masses called bezoars can occasionally develop inside the digestive system.
Understanding how these problems arise may help families recognize when further medical attention is appropriate.
When an ordinary symptom becomes a daily burden
Abdominal pain is one of the common reasons children and teenagers visit healthcare professionals.
The possible causes range from relatively minor digestive disturbances to more complicated medical conditions.
Constipation, for example, can create discomfort that appears and disappears over several days. A stomach infection may cause cramping, nausea, and temporary changes in bowel movements. Food intolerances can produce bloating or abdominal pain after particular meals.
Other possibilities include acid-related disorders, celiac disease, inflammatory bowel disease, urinary tract problems, and certain reproductive health conditions.
In some young people, recurring pain is classified as a functional abdominal pain disorder, meaning symptoms arise from disturbances in gut function or gut-brain communication rather than an identifiable structural abnormality. The pain in these conditions is real and may be severe.
What makes the evaluation challenging is that different conditions can produce similar symptoms.
A teenager may initially report a dull ache near the middle of the abdomen. Weeks later, the discomfort might become more frequent, particularly after eating. Another patient may experience nausea or feel full after consuming only a small amount of food.
These observations are important, but none is sufficient to establish a diagnosis on its own.
Doctors must consider the location of the pain, its duration, associated symptoms, the patient's overall growth and development, and findings from the physical examination.
One child with recurring abdominal pain may need reassurance, symptom management, and follow-up. Another may require laboratory investigations or imaging. A third may need urgent surgical evaluation.
The difference becomes clearer through careful assessment rather than assumptions.
The emotional impact of unexplained symptoms
Persistent pain can also affect a teenager's emotional well-being.
Adolescence is a period when friendships, independence, school performance, and social confidence become increasingly important.
Missing classes or declining invitations because of an unpredictable stomachache can leave a young person feeling isolated. Repeated visits to medical appointments may create anxiety, especially when initial examinations do not reveal a clear explanation.
Parents may feel equally uncertain.
They want to believe that the problem is temporary, but they may become concerned when familiar remedies do not help or symptoms continually return.
Some teenagers hesitate to describe their discomfort because they do not want attention. Others worry that adults will assume they are exaggerating.
For this reason, the way families respond can make a difference.
Listening carefully, acknowledging the child's experience, and describing symptoms accurately to a healthcare professional can support more effective assessment.
Keeping track of when the pain occurs, what makes it worse, and whether other symptoms appear may provide useful information.
It is also important to remember that the absence of an immediate diagnosis does not mean the pain is imaginary.
Some conditions become clearer over time. Others require a particular test or specialist evaluation before their cause can be identified.
Why six months should raise questions
A six-month period of recurring abdominal discomfort is not automatically a sign of a dangerous disease. Many young people experience chronic abdominal symptoms without having a surgical condition.
However, persistent symptoms should not be dismissed simply because they have become familiar.
Pain that interferes with eating, sleeping, attending school, or participating in everyday life deserves medical attention and, when necessary, reassessment.
A particularly important concern is whether additional warning signs have developed.
Unintentional weight loss, persistent vomiting, blood in the stool, a growing abdominal swelling, unexplained fever, or difficulty maintaining normal hydration can change how urgently a patient needs to be evaluated.
The goal is not to frighten families into believing that every stomachache hides a serious condition.
Instead, it is to recognize that prolonged symptoms tell doctors something important: further questions may need to be answered.
And in rare circumstances, the explanation may involve something that has gradually accumulated inside the digestive tract.
Chapter 2: The Unexpected Possibility—What Can Accumulate Inside the Stomach?
When people think about stomach problems, they usually imagine inflammation, excess acid, an infection, or something they ate.
Few consider the possibility that a solid mass of accumulated material might be occupying space inside the stomach itself.
Yet such masses exist.
Doctors refer to them as bezoars , a medical term describing compact collections of material that remain within the digestive system instead of passing through normally.
According to the Merck Manual, bezoars most commonly form in the stomach and may contain substances that are partially digested or cannot be digested effectively.
Some consist of plant fibers. Others develop from medications or different types of swallowed material.
One particularly unusual type is made of hair.
It is known as a trichobezoar .
What exactly is a trichobezoar?
A trichobezoar is a tightly packed collection of hair that accumulates within the stomach.
Human hair contains keratin, a strong structural protein that the digestive system cannot efficiently break down.
When someone swallows small amounts of hair, the material may sometimes pass through the gastrointestinal tract without causing an obvious problem.
However, repeated ingestion can allow strands to become tangled and trapped inside the stomach.
Over time, additional strands may attach to the existing material.
Food particles and mucus can become mixed into the growing mass, producing a dense collection that may occupy an increasingly large portion of the stomach.
Unlike ordinary food, which is processed and moved onward through the intestines, accumulated hair can resist digestion and remain in place.
The resulting mass may gradually interfere with the stomach's ability to function normally.
For some patients, this process develops without immediately producing dramatic symptoms.
In others, nausea, abdominal discomfort, a reduced appetite, or a feeling of fullness may appear.
The mass can also contribute to complications if it becomes large enough to obstruct the normal movement of food.
The Cleveland Clinic identifies abdominal pain and constipation among possible symptoms associated with trichobezoars and explains that large accumulations may interfere with digestion.
Why can a hair mass become so large?
The stomach is designed to mix food with digestive juices and gradually move its contents into the small intestine.
Its muscular walls repeatedly contract to break down food and propel it onward.
But hair behaves differently from most dietary substances.
It does not dissolve readily in stomach acid, and its long, flexible strands can become entangled.
As more hair collects, the strands may form a dense structure that resists the normal movements of the stomach.
The shape of the mass can sometimes reflect the space in which it developed.
In reported medical cases, surgeons have removed trichobezoars that occupied substantial portions of the stomach.
Some masses have extended beyond the stomach into the small intestine.
This is one reason a rare condition involving swallowed hair can eventually require invasive medical treatment.
However, the size, appearance, and composition of any mass cannot be reliably established from an isolated online photograph.
An unusual object shown in a viral image could represent different materials, and photographs may be separated from their original clinical context.
The diagnosis must come from medical evidence, not visual resemblance alone.
The rare condition called Rapunzel syndrome
One of the most unusual complications associated with trichobezoars is known as Rapunzel syndrome .
The name comes from the fairy-tale character Rapunzel, famous for her exceptionally long hair.
In this medical condition, a large hair mass forms within the stomach and extends through the stomach's outlet into the intestine.
The resulting structure can resemble a long tail of tangled material.
Rapunzel syndrome is rare, but it is well documented in medical literature.
Its symptoms may include abdominal pain, nausea, vomiting, reduced appetite, and difficulties related to obstruction.
A published pediatric surgical case series described seven patients with trichobezoars ranging in age from 5 to 23 years. Five had extensions beyond the stomach's outlet, and all seven underwent surgery.
These findings come from a small, selected group of patients and should not be interpreted as estimates of how frequently the condition occurs in the general population.
The dramatic appearance of such masses explains why photographs sometimes attract public attention.
Yet the medical significance goes beyond their unusual appearance.
A large mass may disrupt normal digestion, irritate tissues, prevent adequate food intake, or create an obstruction.
If left untreated in a severe case, complications can become dangerous.
How swallowing hair can be connected to behavior
One sensitive aspect of trichobezoars involves the circumstances in which hair may be swallowed.
Some individuals experience trichophagia , a condition involving recurring urges to eat hair.
It can occur alongside trichotillomania , a disorder characterized by repeated hair pulling.
These behaviors are not simply matters of someone choosing to do something unusual.
They may be associated with difficult-to-control urges, emotional distress, or other mental health concerns.
Not everyone who pulls their hair swallows it, and not everyone who swallows hair develops a trichobezoar.
Likewise, discovering a trichobezoar does not justify making unsupported assumptions about a patient's personality, family circumstances, or psychological history.
Medical professionals approach these issues by understanding the individual's symptoms and behavior rather than relying on judgment or blame.
A teenager who experiences urges to pull or swallow hair may hide the behavior because of embarrassment or fear of criticism.
That secrecy can make it difficult for parents or doctors to identify a possible connection with digestive symptoms.
Supportive conversation is therefore essential.
When hair-eating behavior is suspected, clinicians may recommend a combination of medical evaluation and mental health treatment.
Cognitive behavioral approaches and other therapies can help patients understand triggers, recognize urges, and develop alternative responses.
Not every abdominal mass is made of hair
Although trichobezoars receive attention because of their appearance, they represent only one category of bezoars.
Phytobezoars, for example, consist primarily of difficult-to-digest plant material such as fibers, seeds, and fruit skins.
Other bezoars may form from certain medications or different ingested substances.
Factors such as delayed stomach emptying, prior digestive surgery, and other medical conditions can increase the likelihood of certain bezoars forming.
These distinctions matter because treatment varies with the type of material involved.
Some plant-based bezoars may respond to carefully supervised medical treatment or endoscopic removal.
Hair-based masses are generally more resistant to attempts to dissolve them and may require mechanical removal, particularly when large.
Families should never attempt to treat a suspected bezoar with homemade solutions, excessive laxatives, or internet remedies.
A blockage or significant mass requires proper diagnosis, and an inappropriate treatment could delay necessary care.
The difference between a striking photograph and a medical diagnosis
The original story's image may create an immediate impression that doctors discovered a large, tangled object.
But compelling visual evidence is not the same as a confirmed clinical record.
To establish what happened to a particular patient, readers would need information such as a documented diagnosis, hospital or publication details, and an account of the procedure.
Without these, it is impossible to determine whether the material shown was definitely a trichobezoar, whether the girl had Rapunzel syndrome, or whether the photographed specimen even belongs to the same case.
The appropriate conclusion is therefore measured.
The image raises a legitimate medical possibility, but it cannot independently prove the explanation.
What makes the topic valuable is that the underlying medical conditions are real, recognized, and potentially serious.
Understanding those conditions can help turn a sensational headline into useful health knowledge.
Chapter 3: How Doctors Investigate Persistent Abdominal Pain
When abdominal pain lasts for months, finding the cause can involve several steps.
A medical investigation rarely begins with surgery. Instead, doctors generally start with the least invasive methods that can provide useful information.
This approach helps protect patients from unnecessary procedures while allowing healthcare professionals to identify conditions that need urgent attention.
In the case of a teenager with unexplained pain, the first step is often a detailed conversation.
Understanding the patient's medical history
Doctors begin by asking how long the symptoms have been present and how they have changed.
A patient may be asked whether the pain occurs every day, appears at particular times, or comes in unpredictable episodes.
The location of the discomfort can also offer clues.
Pain concentrated in the upper abdomen may suggest different possibilities from pain occurring in the lower-right abdomen or throughout the entire stomach area.
However, abdominal organs share complex nerve pathways, and pain may not always appear directly over the affected organ.
Clinicians therefore consider the overall pattern rather than relying on location alone.
Other questions may focus on eating habits.
Does the teenager feel full after only a few bites? Is nausea more noticeable after meals? Has appetite decreased? Have there been changes in weight?
A feeling of early fullness can be especially relevant when doctors are considering conditions that interfere with normal stomach emptying.
Changes in bowel movements also matter.
Constipation, diarrhea, blood in the stool, or an inability to pass gas may point toward different digestive problems.
Doctors may ask about medication use, previous illnesses, family medical history, and any changes in daily routines.
Depending on the patient's age, symptoms, and circumstances, clinicians may privately discuss menstrual and reproductive health, sexual health, substance exposure, or mental health concerns where medically appropriate.
These questions are not intended to embarrass the patient.
They help distinguish between conditions that might otherwise appear similar.
For an adolescent, private and respectful communication can be particularly important because some symptoms or behaviors may be difficult to discuss in front of family members.
What doctors look for during an examination
The physical examination provides another essential part of the assessment.
A clinician may gently examine different regions of the abdomen, looking for tenderness, swelling, guarding, or an unusual mass.
They may listen for bowel sounds and evaluate whether the abdomen appears distended.
General observations can also be important.
Signs of dehydration, pallor, weakness, weight loss, or poor growth may influence the investigation.
A teenager who has experienced months of poor appetite may need assessment of nutritional status, particularly if the discomfort has reduced normal food intake.
In some cases, doctors can detect a palpable abdominal mass.
However, not all masses can be felt through the abdominal wall, and the absence of an obvious lump does not rule out a digestive condition.
Similarly, a normal examination does not guarantee that every possible cause has been excluded.
It means that the findings must be interpreted alongside the medical history and any other available evidence.
Blood tests and other laboratory investigations
Laboratory testing may help identify inflammation, anemia, infection, nutritional deficiencies, or other abnormalities.
For example, a complete blood count can provide information about red and white blood cells.
Low hemoglobin may suggest anemia, which can occur for a variety of reasons and requires further interpretation.
Tests measuring inflammation may sometimes support the investigation of certain diseases, although they cannot identify a trichobezoar by themselves.
Depending on the situation, clinicians may also assess kidney and liver function, electrolyte balance, urine findings, or conditions such as celiac disease.
Not every teenager needs all of these investigations.
Doctors choose tests based on symptoms and clinical findings rather than ordering every available procedure automatically.
This principle helps reduce unnecessary discomfort, cost, and confusion.
The role of ultrasound and medical imaging
When a structural problem is suspected, imaging can provide valuable information.
Ultrasound is frequently useful in children because it creates images using sound waves rather than ionizing radiation.
It can help clinicians assess certain abdominal organs and investigate possible causes of pain.
Nevertheless, ultrasound has limitations.
Gas within the intestines, the patient's anatomy, and the location of an abnormality can affect what is visible.
An inconclusive ultrasound does not necessarily mean that nothing is wrong.
Computed tomography, commonly called a CT scan, creates detailed cross-sectional images of the body.
CT imaging can help identify certain masses, obstructions, inflammatory processes, and other abnormalities.
However, it exposes patients to ionizing radiation, so doctors carefully consider its benefits and risks, especially for children and adolescents.
Magnetic resonance imaging, or MRI, may provide an alternative for some conditions without using ionizing radiation.
The National Institute of Diabetes and Digestive and Kidney Diseases describes ultrasound, CT, and MRI as tools clinicians may use when evaluating abdominal conditions such as appendicitis, with the choice influenced by patient characteristics and clinical needs.
The central lesson is that imaging should answer a specific medical question.
An investigation is most useful when doctors understand what they are looking for and how the result will affect treatment.
When an endoscopy may be necessary
For certain stomach conditions, doctors may recommend an upper gastrointestinal endoscopy.
During this procedure, a specialist passes a thin, flexible instrument with a camera through the mouth and into the upper digestive tract.
The procedure allows doctors to examine the lining of the esophagus, stomach, and first part of the small intestine.
It can help identify inflammation, ulcers, bleeding, foreign material, or unusual masses.
In some cases, instruments passed through the endoscope can also retrieve or break apart material.
For a suspected bezoar, endoscopy may provide direct confirmation of what the mass contains.
But endoscopy does not always offer an effective method of removal.
A large, densely packed trichobezoar may be difficult to fragment or extract safely through the endoscope.
If the material is too large or extends into the intestine, surgical treatment may be necessary.
The Merck Manual notes that management depends on the bezoar's composition, size, symptoms, and associated complications.
Why surgery sometimes becomes the safest option
The decision to operate is never based solely on how unusual an object looks in a photograph.
Doctors consider whether the patient's condition can be managed safely through less invasive means.
Surgery may become necessary when a mass creates an obstruction, causes complications, or cannot be removed adequately through endoscopy.
In some cases, surgeons may use minimally invasive techniques involving small incisions and specialized instruments.
In others, especially when a mass is very large or complicated, an open surgical procedure may be more appropriate.
The operation may involve opening the stomach to remove the accumulated material and then carefully closing the surgical opening.
Surgeons also assess surrounding tissues and may examine the intestine for additional material or complications.
The exact approach depends on the individual patient.
It would be inappropriate to assume which procedure the reported 14-year-old underwent without verified medical documentation.
What is clear from published cases is that surgical removal can be an effective treatment for significant trichobezoars.
For example, a case report published in BMJ Case Reports described a patient with Rapunzel syndrome whose large hair mass was removed through abdominal surgery after it caused partial obstruction of the stomach's outlet.
Such reports demonstrate that the condition is medically real, although they do not establish the circumstances of the viral story.
Recovery involves more than removing the mass
Successful surgery addresses the immediate physical problem, but recovery may require additional care.
Doctors monitor patients for complications, assess pain control, and determine when food and fluids can be safely resumed.
If poor nutrition, anemia, dehydration, or other problems developed before treatment, these may need to be addressed.
Follow-up appointments help clinicians assess healing and recognize any returning symptoms.
When a trichobezoar is linked to hair-eating behavior, attention to the underlying behavior is especially important.
Removing the existing mass does not necessarily prevent another from developing if the contributing behavior continues.
A multidisciplinary team may therefore include pediatricians, surgeons, gastroenterologists, mental health professionals, dietitians, and family caregivers.
The objective is not simply to resolve one dramatic medical event.
It is to support the young person's long-term physical and emotional health.
Chapter 4: Why Early Medical Attention Can Make a Difference
One of the most valuable lessons from reports of prolonged abdominal pain is that symptoms should be taken seriously without immediately assuming the worst.
Most stomachaches do not represent medical emergencies.
Children may experience discomfort related to ordinary infections, constipation, dietary changes, or other manageable conditions.
Yet certain patterns deserve closer attention.
The challenge for families is understanding when observation is reasonable and when professional care is necessary.
Symptoms that deserve urgent evaluation
Severe or rapidly worsening abdominal pain should not be ignored.
Pain accompanied by a rigid or markedly swollen abdomen, repeated vomiting, or an inability to pass stool or gas can indicate a significant abdominal problem.
Vomiting blood, passing bloody or black stools, fainting, or developing signs of severe dehydration also requires urgent assessment.
Green, bile-colored vomiting is another particularly concerning symptom, especially when accompanied by abdominal distension or severe pain.
A child who appears unusually weak, confused, or seriously ill should receive prompt medical attention.
These symptoms do not automatically indicate a bezoar.
They may arise from several different conditions, some of which require immediate treatment.
Families should seek emergency medical care rather than waiting for symptoms to disappear or attempting to manage a possible obstruction at home.
Why changes in eating habits matter
One symptom that parents sometimes overlook is a significant change in appetite.
Teenagers naturally have variable eating habits, and occasional appetite fluctuations are not unusual.
However, a persistent inability to finish meals or an ongoing feeling of fullness after eating small amounts deserves discussion with a healthcare professional.
The stomach normally expands as food enters and gradually empties into the small intestine.
When that process becomes disrupted, a person may experience nausea, pressure, bloating, or early satiety.
A large gastric bezoar is one possible explanation, but many other conditions can create similar symptoms.
The important question is whether the change persists and whether it affects nutritional intake or weight.
Unintentional weight loss, fatigue, or difficulty maintaining normal growth can provide additional reasons for evaluation.
The value of a simple symptom diary
Families do not need sophisticated medical equipment to collect useful information.
A basic record can help reveal patterns that are difficult to remember during an appointment.
For example, a parent might record the time pain begins, how long it lasts, where it is located, and whether it occurs before or after meals.
Other observations could include nausea, vomiting, bowel movements, fever, sleep disruption, or missed school activities.
Recording medications and their effects can also be helpful.
The purpose is not to diagnose the child at home.
Instead, the record creates a clearer picture for the healthcare professional.
It can also help identify changes in the condition over time.
A symptom diary should remain simple and should never delay urgent treatment when serious warning signs are present.
Why families should avoid self-diagnosis
The internet offers immediate access to descriptions of thousands of medical conditions.
This can help people understand unfamiliar terminology, but it can also create unnecessary fear.
A parent searching for persistent stomach pain may encounter explanations ranging from constipation to rare tumors or unusual gastrointestinal masses.
Reading about a frightening surgical case can make a common symptom appear far more dangerous than it usually is.
Conversely, online advice may encourage people to dismiss potentially serious symptoms as ordinary indigestion.
Neither extreme is helpful.
A medical diagnosis depends on a combination of history, examination, testing when indicated, and professional interpretation.
A viral photograph cannot replace that process.
Families should also avoid trying treatments designed for conditions that have not been diagnosed.
A suspected bowel obstruction, for example, should not be managed with aggressive home remedies.
The safest response to persistent or worsening symptoms is appropriate medical assessment.
Creating an environment where teenagers feel comfortable speaking
Young people do not always communicate discomfort in a straightforward way.
Some describe themselves as tired instead of admitting they are in pain.
Others lose interest in meals, stop participating in activities, or become unusually withdrawn.
Adolescents may also hesitate to discuss bowel habits or behaviors that they find embarrassing.
Parents can help by asking calm, specific questions without criticism.
Rather than dismissing a complaint, they can ask how often it occurs, whether it has changed, and what activities it affects.
Open conversation is particularly important when symptoms may be associated with emotional distress or repetitive behaviors.
A teenager struggling with hair pulling or hair eating may need professional assistance, not punishment.
Shame can make such behaviors harder to disclose.
A supportive environment allows the medical team to gather more accurate information and helps the patient participate in treatment.
Physical symptoms and emotional health are connected
Pain can affect mood, and emotional distress can influence how pain is experienced.
This relationship is especially relevant in adolescents because the digestive system and nervous system communicate continuously.
Stress and anxiety may intensify certain gastrointestinal symptoms, while chronic physical discomfort can increase emotional distress.
However, clinicians should not automatically attribute persistent abdominal pain to stress.
Psychological factors and physical medical conditions can coexist.
A teenager may experience anxiety because of repeated pain, while also having an underlying digestive disorder that requires treatment.
Both aspects deserve attention.
A comprehensive healthcare approach respects the patient's physical complaints while recognizing the emotional consequences of prolonged illness.
For children whose pain does not improve despite initial treatment, follow-up and further evaluation may be appropriate.
Early attention can help identify problems, reduce unnecessary suffering, and support a safer path toward recovery.
Chapter 5: The Lesson Behind the Story—Listening Before a Small Problem Becomes a Larger One
At first glance, the story of a 14-year-old girl experiencing months of abdominal pain may seem like another extraordinary medical mystery.
The possibility that surgeons discovered an unusual mass inside her digestive system is certainly attention-grabbing.
But beyond the headline lies a lesson that applies to families everywhere.
Persistent pain deserves attention, and recognizing changes in a child's health can be an important part of obtaining appropriate medical care.
Why unusual medical stories attract attention
People are naturally fascinated by medical discoveries that seem difficult to believe.
A large mass of tangled hair inside the stomach is particularly striking because it challenges assumptions about how the digestive system works.
Most people understand that the stomach processes food. Fewer realize that certain swallowed materials can accumulate rather than being digested or expelled normally.
When a photograph shows an unusual object reportedly removed during surgery, the image may be shared thousands of times.
Unfortunately, the medical details accompanying such photographs are not always complete.
The patient's identity, the circumstances of treatment, or even the diagnosis may be missing.
Stories may be shortened, translated, or repeated without reliable documentation.
That is why responsible reporting should distinguish between confirmed medical knowledge and unverified details about an individual patient.
In the present story, the claim that a teenager experienced pain for six months and underwent surgery remains a reported account rather than an independently confirmed case history.
The discussion of trichobezoars provides medically documented context, but it should not be mistaken for proof of what happened to this particular girl.
What families can learn about persistent symptoms
The most practical lesson is simple: children should feel comfortable telling adults when something hurts.
Parents and caregivers should take repeated complaints seriously, particularly when symptoms begin interfering with normal activities.
That does not mean every episode of pain requires extensive testing.
It means that continuing or changing symptoms deserve thoughtful assessment.
A clinician may determine that the cause is common and manageable. Another patient may require additional investigations or referral to a specialist.
The appropriate response depends on the individual circumstances.
What matters is avoiding two mistakes: assuming that every stomachache signals a catastrophe, and assuming that prolonged discomfort must be harmless because it has been present for months.
Both assumptions can interfere with good decisions.
Treatment should address the whole patient
When a serious digestive condition is identified, treatment should extend beyond the immediate procedure whenever necessary.
Surgery may remove an obstructing mass, but the patient may also require nutritional support, follow-up examinations, and emotional care.
If the condition is associated with repetitive hair swallowing, appropriate behavioral or psychological treatment can help reduce the risk of recurrence.
It is essential to approach these issues compassionately.
A teenager should not be defined by a medical diagnosis or by behaviors they may struggle to control.
The purpose of treatment is to improve health, relieve distress, and build skills that support long-term recovery.
Families, healthcare professionals, and patients can work together to make that possible.
A reminder about the importance of early intervention
One of the most difficult aspects of chronic symptoms is that they can gradually become part of everyday life.
A child may adjust to discomfort, avoid certain foods, or stop participating in activities without realizing how much their routine has changed.
Parents may also become accustomed to hearing that their child has another stomachache.
This gradual normalization can make it harder to recognize when additional medical attention is needed.
Early intervention does not always mean discovering a dangerous disease.
Sometimes it means diagnosing constipation and developing an effective treatment plan. Sometimes it means identifying a food-related condition, managing a functional pain disorder, or addressing another health problem.
In rare circumstances, further assessment may reveal a structural abnormality that requires a procedure or surgery.
The benefit of seeking appropriate care is that treatment can be directed toward the actual cause rather than guesswork.
The message beyond the dramatic photograph
The image associated with the original story may be the feature that captures public attention, but it is not the most valuable part of the discussion.
The real lesson concerns awareness, communication, and timely medical evaluation.
Children should not have to endure persistent pain in silence.
Families should not feel pressured to identify complicated medical conditions by searching for answers online.
And a dramatic photograph should never be treated as sufficient evidence to diagnose a patient.
The digestive system is remarkably complex. Many disorders produce similar symptoms, and accurate diagnosis often requires careful evaluation.
Most cases of abdominal pain will not involve unusual masses or dramatic surgical discoveries.
But some conditions do require medical intervention, and recognizing persistent or concerning symptoms can help patients receive that care.
Final Thoughts
The reported story of a 14-year-old girl who endured six months of stomach pain before an unexpected surgical discovery is a powerful reminder of how important it is to pay attention to ongoing symptoms.
Although the exact circumstances of her reported case have not been independently verified, the medical conditions discussed here—including trichobezoars and the rare Rapunzel syndrome—are genuine and documented.
They demonstrate how unusual material can sometimes accumulate inside the digestive tract and create complications that require specialized treatment.
For parents, the takeaway is not fear. It is attentiveness.
Listen when a child repeatedly reports pain. Notice changes in appetite, weight, energy, and everyday activities. Seek professional assessment when symptoms persist, worsen, or are accompanied by warning signs.
For teenagers, the message is equally important: speaking up about persistent discomfort is a responsible step toward protecting your health.
And for everyone encountering dramatic medical stories online, the most useful question is not simply what doctors might have discovered during surgery.
It is what reliable medical knowledge can teach us about recognizing problems, seeking appropriate help, and supporting recovery.
Sometimes, the most important discovery begins not in an operating room, but with someone taking a persistent symptom seriously.
Medical Sources and References
The following references support the medical explanations in this article. They do not independently verify the identity, surgical findings, or diagnosis of the 14-year-old described in the original viral account.





